Specialist Mohs surgery on the hand by Consultant Plastic Surgeon Miss Rakhee Nayar, who also holds the European Board of Hand Surgery Diploma. The repair is planned around how you use your hand, as part of the same procedure.
of 36 patients would recommend Miss Nayar (PHIN, September 2026)
Specialist care for the hand
Specialised Mohs Surgery on the Hand
Skin cancer on the hand needs a different approach from skin cancer on the face. The skin is thin, the tendons that move the fingers sit just beneath it, and you use your hands for almost everything you do.
Miss Rakhee Nayar is one of fewer than 10 women in the UK dual-trained in both plastic surgery and Mohs micrographic surgery, and she also holds the European Board of Hand Surgery Diploma. She removes the cancer, checks every margin under the microscope and repairs the hand herself, with movement and grip in mind from the start.
A demanding site
Why is Mohs Surgery Used on the Hand?
The back of the hand is exposed to the sun for a lifetime, which makes it a common site for skin cancer. Squamous cell carcinoma is the most common type here, and basal cell carcinoma also occurs.
There is very little spare skin on the back of the hand. The tendons that straighten the fingers lie just under it, along with nerves and veins.
Standard excision removes the cancer with a fixed margin of healthy skin around it. On the hand, that extra margin can leave a wound that is hard to close without exposing tendon or limiting movement.
Mohs micrographic surgery removes only the tissue that is actually involved, which is why it suits this site.
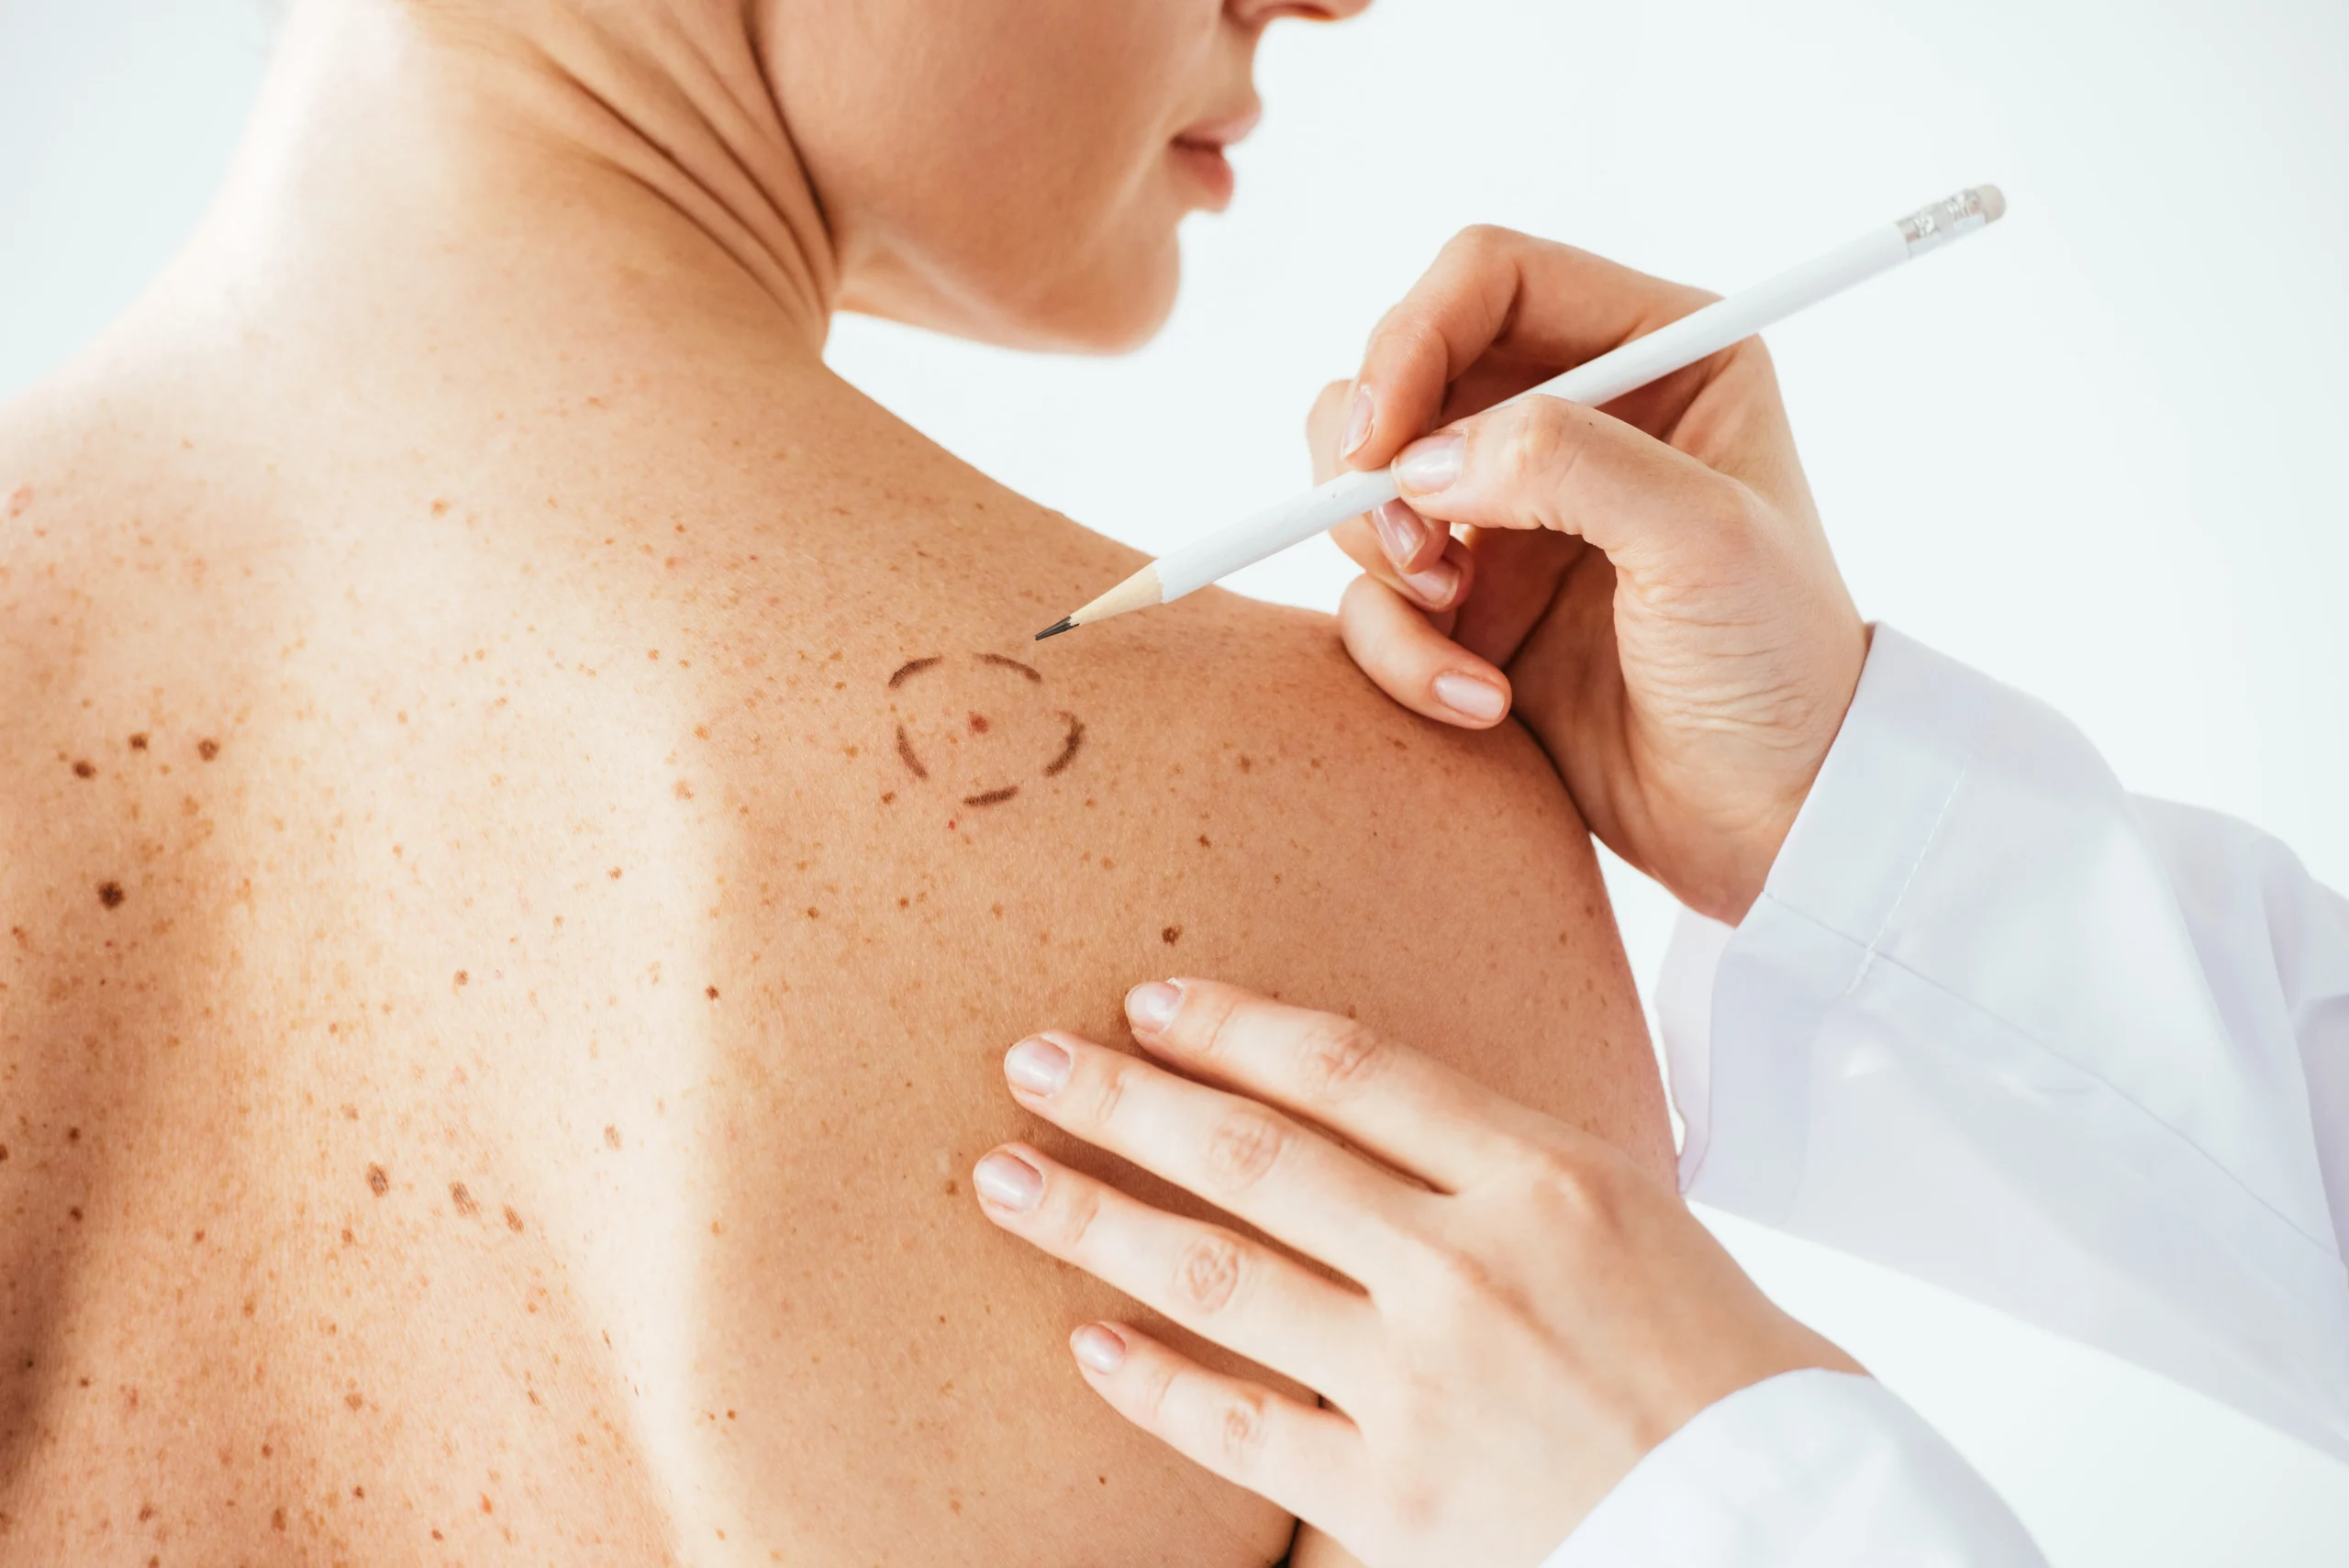
It removes the cancer while keeping as much healthy skin as possible.
Miss Rakhee Nayar removes the cancer layer by layer, checking each one under the microscope while you wait.
Further tissue is taken only where the microscope shows cancer remains, so healthy skin, tendon and nerve are left alone.
A smaller wound is simpler to repair, which makes it easier to keep full movement and grip.
Every margin checked
What Makes Mohs Surgery Suited to the Hand?
Mohs surgery combines removal and microscope checking in one procedure. Each layer is mapped and examined before any more tissue is taken.
With standard excision, the tissue is sent away and the result comes back days later. With Mohs, the margins are confirmed clear before your wound is repaired.

Complete Margin Examination
The whole edge of each layer is examined under the microscope while you wait, so the result is known before the repair begins.
Tissue Sparing
Only the tissue that contains cancer is removed, preserving the limited skin over the tendons and knuckles.
Repair on the Same Day
Once the margins are clear, the wound is usually repaired in the same visit, without a second operation.
Movement Protected
A smaller wound means a simpler repair, planned so the fingers and wrist keep moving freely.
Clinical background
Why Choose Miss Rakhee Nayar for Hand Skin Cancer?
Who treats a skin cancer on your hand matters for how well the hand works afterwards. With over 20 years of surgical experience, Miss Rakhee Nayar brings training in skin cancer surgery, plastic surgery and hand surgery to the same operation.
Hand Surgery Training
Alongside her plastic surgery and Mohs training, Miss Nayar holds the European Board of Hand Surgery Diploma, a specialist examination in surgery of the hand and wrist.
That training shapes how she plans a repair. She considers how tendons glide, how joints bend and how scars behave over the knuckles, not only how to cover the wound.
She is one of fewer than 10 women in the UK dual-trained in both plastic surgery and Mohs micrographic surgery.

The Dual-Specialist Advantage
This combination means the person who removes your cancer is the same person who plans and carries out the repair. Miss Nayar is accredited as both a Consultant Plastic Surgeon and a Mohs surgeon.
- Cancer removal with every margin checked
- Repair planned around tendon and joint movement
- One consultant from consultation to follow-up
- Hand surgery training (EBHS Diploma)
Training and Appointments
Miss Nayar is a Consultant Plastic Surgeon at Mersey and West Lancashire Teaching Hospitals NHS Trust, and sees private patients at Circle Cheshire Clinic and Fairfield Independent Hospital.
- She chairs the Mohs Surgery Training Interface Group (JCST), the national committee for Mohs fellowship training in the UK.
- She holds an MBChB with Honours and an MD from the School of Cancer Studies at the University of Liverpool.
- She is a Fellow of the Royal College of Surgeons of Edinburgh (FRCS Plast) and holds the European Board of Hand Surgery Diploma (EBHS).
- She is an active member of the British Association of Plastic, Reconstructive and Aesthetic Surgeons (BAPRAS) and the British Medical Association.
Specialised care
Hand Conditions and Locations Treated
Basal Cell Carcinoma (BCC)
Squamous Cell Carcinoma (SCC)
The Back of the Hand
Fingers and Knuckles
The Wrist and Forearm
Request an e-Consultation
Miss Nayar offers a convenient e-Consultation service for patients seeking a specialist opinion from across the UK and overseas. This secure digital pathway enables remote assessment of skin lesions and concerns, providing a prompt clinical recommendation.
It is an ideal first step for those considering Mohs surgery or reconstruction before travelling for an in-person appointment.
State-of-the-art technique
Mohs Surgery on the Hand Procedure
Many patients ask whether the procedure will be uncomfortable. Miss Rakhee Nayar uses a gentle, step-by-step approach so you stay comfortable and know what is happening throughout.
Years of surgical experience
Will I feel any pain? The hand is numbed with local anaesthetic, so you stay awake but should not feel pain during removal or repair.
The anaesthetic is given slowly to keep it as comfortable as possible, and it can be topped up at any stage if you feel anything.
Once the skin is numb, the visible cancer is removed with a thin layer of surrounding tissue, which is mapped and sent to the laboratory on site.
While you wait, the tissue is processed and examined under the microscope to check whether any cancer remains at the edges.
Each stage is explained as it happens, and the repair begins only once the margins are confirmed clear.
Protecting movement and appearance
Reconstructive Procedure after Mohs Surgery on the Hand
Removing the cancer is the first goal. The second is a repair that lets you use your hand normally again. Miss Rakhee Nayar chooses the repair to suit the size and site of the wound and the way you use your hand.
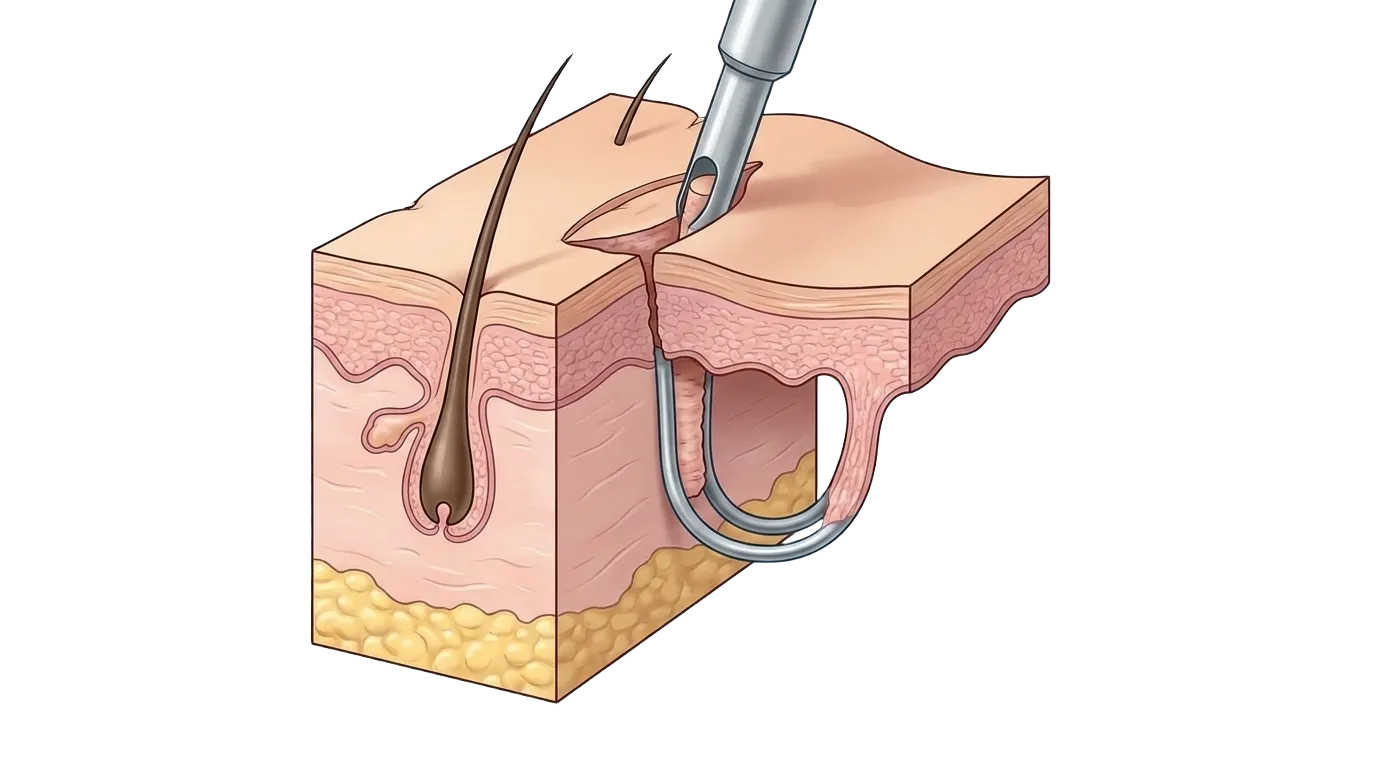
Direct Closure
Small wounds can often be closed with a neat line of stitches, placed along the natural creases of the hand where possible.
Skin Grafts
Where there is not enough loose skin to close the wound, a thin piece of skin is taken from another site and placed over it.
Local Flaps
Neighbouring skin can be moved across to cover the wound while keeping its own blood supply, giving a good match in thickness and texture.
Planned Around Movement
Every repair is planned around tendon glide and joint movement, so the hand can bend and grip once it has healed.
Getting back to normal
Recovery and Long-Term Results
Once the cancer has been removed and the hand repaired, the focus moves to healing. Miss Rakhee Nayar gives you a clear aftercare plan and sees you again to check the repair.
- Keeping the hand raised for the first couple of days reduces swelling and discomfort.
- A bulky dressing, and occasionally a light splint, protects the repair for the first few days. The wound needs to stay dry until it has sealed.
- Light use usually returns within days, and desk work tends to resume quickly. Heavier lifting and gripping wait until the repair has healed.
- Driving is sensible again once you can grip the wheel comfortably and react normally.
- Some stiffness in the early weeks is common and usually temporary. Scars start pink and firm, then soften and fade over several months.
- Regular skin checks and high-factor sun protection on the backs of the hands help to catch or prevent new skin cancers.

In Patients' Words
Patients Feedback



What Our Patients Say
Concerned About Skin Cancer?
Book a Specialist Assessment
Early assessment usually means a smaller operation and a simpler repair. Contact Miss Rakhee Nayar’s clinic for an assessment by a consultant dual-trained in Mohs and plastic surgery.
or Call Us Now
07740 306144
Circle cheshire Clinic
The Courtyard, Hall Ln, Wincham, Northwich CW9 6DG, United Kingdom
07740 306144
contact@mohssurgeon.co.uk
Schedule Your Visit
Where to See Miss Nayar
Miss Rakhee Nayar provides specialist Mohs and reconstructive surgery at Circle Health Cheshire Clinic. This modern, private facility offers expert care in a discreet environment for patients across Cheshire and the North West.


Frequently Asked Questions
We're Always Here to Help You
Will I be able to use my hand straight away?
You can use your hand lightly soon after the procedure, but it is best to rest it and keep it raised for the first couple of days. Heavier use waits until the repair has healed, and Miss Nayar will tell you what to expect for your type of repair.
Will I need a splint?
Most patients do not. A light splint is occasionally used for a few days to protect a repair over a joint or knuckle.
When can I drive?
Once you can grip the steering wheel comfortably and react normally. For smaller repairs this is often within a few days. If the repair crosses a joint, it may take longer.
Will I be awake for the surgery?
Yes. The procedure is carried out under local anaesthetic, so you stay awake and can talk to the team throughout. It also avoids the need for a general anaesthetic.
How long will the surgery take?
It depends on how many layers are needed, which cannot be known in advance. Plan to be at the clinic for at least half a day. Larger or more complex cancers can take longer.
Will Mohs reconstruction leave a scar?
All surgery leaves a scar. Miss Nayar’s plastic surgery training shapes the repair: she uses fine stitching and places scars along the natural lines of the hand where possible, so they settle well over time.