
Aesthetic outcomes in facial surgery after skin cancer removal depend on three things above all: the surgical technique used to clear the tumour, the reconstruction method chosen to close the defect, and how well your expectations are set before you go into theatre. Get all three right, and the scar you live with long-term is far better than most patients anticipate. Miss Rakhee Nayar, GMC-registered Consultant Plastic Surgeon (FRCS Plast, MD) and dual-trained Mohs surgeon, works within this framework for every patient she treats at Circle Cheshire.
The main factors that shape your facial surgery results are:
- Tumour clearance method: Mohs micrographic surgery preserves the maximum healthy tissue by examining 100% of the surgical margin in stages, keeping more reconstructive options open than standard excision.
- Reconstruction technique: primary closure, skin grafts, and local flaps each produce different scar qualities, colour matches, and functional outcomes.
- Patient-specific factors: age, skin laxity, skin type, and underlying health conditions all influence how tissue heals and how visible a scar becomes.
- Pre-operative communication: validated tools such as the FACE-Q Skin Cancer Module measure patient-reported satisfaction with appearance, scar appraisal, and psychosocial distress, giving surgeons objective data to guide counselling.
- Post-operative care: scar massage, moisturising, and adjunctive therapies such as laser treatment can meaningfully improve the final appearance over months.
- Psychosocial wellbeing: anxiety about appearance after surgery is clinically significant and should be addressed as part of your care, not treated as an afterthought.
How reconstruction technique determines your facial surgery results
Choosing the right repair method is where surgical judgement has the greatest impact on cosmetic outcomes. The decision rests on defect size, location, available local tissue, and your general health.
Primary closure
Suturing the wound edges directly is the simplest approach and heals quickly. The limitation on the face, particularly the nose, is that a straight linear scar can cross subunit boundaries or create a bowstring tension effect on convex surfaces. Research on nasal reconstruction found that patients who underwent primary closure were the least satisfied with their post-operative scar compared with those who had flap or graft repairs.
Skin grafts
Split-thickness grafts (STSG) take a thin shaving of skin, usually from the thigh or calf, and heal the donor site within two to three weeks. Full-thickness grafts (FTSG) use the complete skin depth from sites such as behind the ear or the upper arm, and maintain better skin features such as thickness and texture, making them preferable for visible facial areas. FTSG donor sites require a dressing for several days to allow the graft to establish a blood supply. Composite grafts, which include cartilage or other tissue, are reserved for complex areas around the nose or eyelid.
Local flaps
A flap carries its own blood supply, so it does not depend on the wound bed to survive. Flap scars are typically curved and interrupted, which breaks the reflection of light and camouflages the repair far better than a straight closure line. In a study of 128 patients who underwent nasal reconstruction after Mohs surgery, those with flap reconstructions scored 7.8 points higher for scar satisfaction than those with primary closures. Common flaps used on the face include the transposition (rhomboid) flap, the V-Y advancement flap along the nasal sidewall, and regional or free flaps for larger defects requiring tissue from further away.

Pro Tip: For nasal defects in particular, surgeons are increasingly moving away from the traditional reconstructive ladder, which starts with the simplest option. Evidence now supports considering a one-stage flap reconstruction earlier, even for smaller defects, because long-term scar satisfaction is consistently higher.
Adjunctive therapies
Laser resurfacing and injectable fillers can refine cosmetic outcomes once the wound has fully healed, typically after 12 months. These are not substitutes for good primary reconstruction, but they can address residual contour irregularities or persistent redness that scar maturation alone does not resolve.
Scar management and recovery timeline
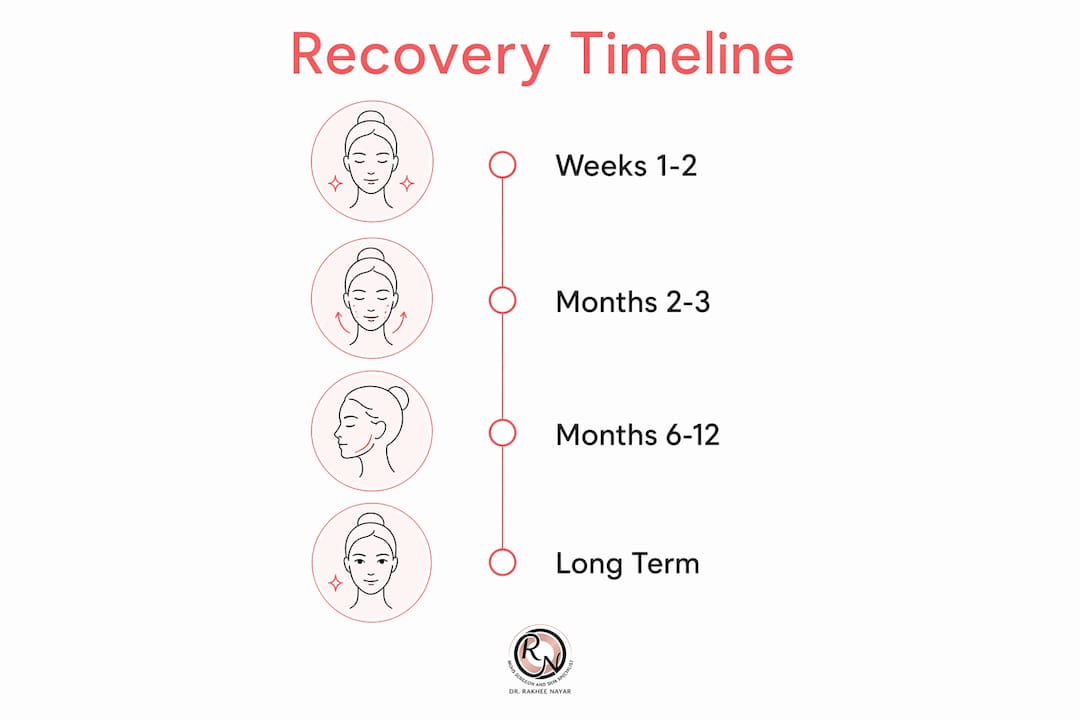
Scars follow a predictable course. In the first two weeks, redness and swelling are normal. By 2–3 months, the scar line appears pink and raised. Between 3 and 12 months, it should fade and flatten. Moisturiser massage applied twice daily for up to four months, starting three to four weeks after surgery, is recommended to soften the scar and reduce tension on the wound edges.
Patient-specific factors
Older patients tend to achieve better cosmetic results. Greater skin laxity in older patients reduces wound tension, provides more local tissue for repair, and means wrinkles and skin folds naturally conceal scars. Younger patients and women statistically report higher psychosocial distress and cancer worry after facial reconstruction, and should be offered additional support proactively.
Communication and expectation management
Consultations that feel rushed are a genuine clinical risk. A BBC News report on a Cumbrian patient’s experience highlighted that inadequate pre-operative discussion left her unprepared for the pain and scarring she experienced. GMC guidance places a clear duty on surgeons to ensure patients understand what to expect. Visual aids, including photographs of previous patients at similar stages of healing, are one of the most effective tools for preparing you for the temporary appearance of swelling and bruising in the first weeks. If your consultation feels insufficient, requesting an additional appointment before surgery is entirely reasonable.
| Factor | Effect on cosmetic outcome |
|---|---|
| Mohs micrographic surgery | Maximises tissue preservation; widens reconstruction options |
| Flap reconstruction | Higher long-term scar satisfaction than primary closure |
| FTSG | Better texture and thickness match for visible facial areas |
| Older age / greater skin laxity | Reduced wound tension; scars concealed by natural folds |
| Scar massage (twice daily, up to 4 months) | Softens and flattens scar over time |
| FACE-Q assessment | Tracks patient-reported satisfaction and psychosocial distress |
The multidisciplinary team approach recommended in NHS clinical guidelines, including Thames Valley Cancer Alliance guidance, is particularly relevant for high-risk tumours on the eyelids, nose, and lips, where reconstruction is most technically demanding and the aesthetic stakes are highest.
Rakhee Nayar – Mohs Surgeon and Skin Specialist: expert facial reconstruction in the North West
Rakhee Nayar – Mohs Surgeon and Skin Specialist offers something genuinely uncommon: a single consultant who performs both the Mohs excision and the reconstruction. That continuity matters. Miss Nayar sees the defect the moment it is created and plans the repair with the full picture in front of her, rather than handing you to a separate team. Her dual training in plastic surgery and Mohs means the decision between primary closure, flap, and graft is made by someone who has done all three at the highest level.
Consultations at Circle Cheshire are unhurried. Miss Nayar uses visual aids and, where appropriate, FACE-Q outcome data to set realistic expectations and discuss the psychosocial aspects of facial reconstruction openly. Private fees are available on request. To discuss your facial reconstruction options or to book a consultation, contact the practice directly through mohssurgeon.co.uk.
This article is for information only and does not constitute medical advice. Consult a GMC-registered specialist for advice specific to your situation.
Key takeaways
Flap reconstruction consistently produces higher long-term scar satisfaction than primary closure for facial defects, particularly on the nose, and should be considered earlier in the decision process than the traditional reconstructive ladder suggests.
| Point | Details |
|---|---|
| Technique drives satisfaction | Flap reconstruction patients scored 7.8 points higher for scar satisfaction than primary closure patients in nasal reconstruction studies. |
| FACE-Q guides counselling | This validated patient-reported outcome measure tracks appearance satisfaction, scar appraisal, and cancer worry to improve shared decision-making. |
| Age affects healing | Greater skin laxity in older patients reduces wound tension and allows natural folds to conceal scars more effectively. |
| Scar care extends results | Twice-daily moisturiser massage for up to four months, starting three to four weeks post-surgery, is recommended to improve the final scar. |
| Miss Nayar’s dual training | Rakhee Nayar – Mohs Surgeon and Skin Specialist performs both Mohs excision and reconstruction, ensuring continuity of aesthetic planning from tumour removal to repair. |
FAQ
What is Mohs micrographic surgery and why does it matter for aesthetics?
Mohs micrographic surgery removes skin cancer in stages while examining 100% of the surgical margin, achieving complete clearance with the smallest possible defect. Preserving healthy tissue directly expands the reconstruction options available, which is particularly important on cosmetically sensitive areas such as the nose, eyelids, and lips.
Which reconstruction gives the best facial surgery results?
Local flap reconstruction generally produces the highest long-term scar satisfaction, especially for nasal defects, because flap scars are curved and interrupted, camouflaging better than straight primary closure lines. Full-thickness skin grafts are a strong second choice where flaps are not feasible, as they maintain better skin texture and thickness than split-thickness grafts.
How long does it take to see the final cosmetic result?
Scars typically take 12 months to fully mature. Redness and swelling settle in the first few weeks, the scar appears pink and raised at 2–3 months, and fading and flattening continue through to 12 months. Scar massage from week three to four onwards supports this process.
Does age affect how well facial reconstruction heals?
Older patients tend to achieve more favourable cosmetic outcomes because greater skin laxity reduces tension on the wound and natural wrinkles and skin folds conceal scars. Younger patients may experience more visible scarring and statistically report higher psychosocial distress after surgery.
What is FACE-Q and how is it used in facial reconstruction?
FACE-Q is a validated patient-reported outcome measure that assesses satisfaction with facial appearance, scar appraisal, and psychosocial distress after reconstructive surgery. Surgeons use it to track outcomes objectively and to improve pre-operative counselling and expectation management.
Recommended
- Cosmetic outcomes in skin cancer surgery explained
- Aesthetic surgery after cancer: options and expert insights
- Facial reconstructive surgery types for better outcomes
- Explaining cosmetic outcomes in Mohs surgery
Filed under Facial Reconstruction